

Categories
Partnerships CSR Partners In Change

A Season to Care: How CRM Shaped Impact in 2025

In 2025, Smile Foundation witnessed the transformative power of brands uniting through cause related marketing (CRM) partnerships to challenge perceptions and create meaningful impact. Compassion driven collaborations demonstrated that CRM is no longer just a promotional tool, as today brands are increasingly seen as accountable, accessible and active social agents. 

Furthermore, through CRM partnerships, consumers experienced the journey of change firsthand- a child gaining access to classroom, an older woman receiving healthcare at her doorstep, a young girl being able to continue her education despite menstrual issues, youth acquiring 21st century skills and women empowered with resources and skills to uplift themselves, their families and communities, proving that Cause Related Marketing is now a crucial tool for businesses to move with purpose and create social change, hand in hand.

Journal of Marketing Research

Strengthening Relationships Beyond Giving

CRM partnerships played a pivotal role in deepening impact by enabling continuity, context and clarity. Every activity was recorded and analysed to create a cohesive lasting strategy that allowed brands to move beyond episodic collaboration. 

Partners engaged with timely insights, impact data and storytelling which reflected their contribution’s real world-outcomes. By aligning organisational memory with human stories from the field, Smile Foundation’s CRM activities ensured that partnerships grow rich over time, rooted in shared learning, transparency and a deepening commitment to beneficiaries.

  • Streamlined Partner Communication and Engagement Journeys 

Effective communication was the backbone of trust-driven partnerships. Smile Foundation’s CRM programme enabled structured and personalised engagement journeys. From onboarding to impact reporting, timely communication and automated workflows supported consistency, while human oversight ensured warmth and empathy in the activities. 

  • Enabled Customised CSR Engagement Aligned with Partner Priorities 

Every brand enters a cause with unique priorities. Smile’s CRM interventions helped in mapping these unique goals precisely with customised engagement models which was then further supplemented with tracking sectoral interests, geographic focus and impact expectations- resulting in making every investment resonate deeply with both corporate objectives and community needs. 

  • Supported Long-Term Partnerships Over One-time Contributions 

Sustainable social change demands consistency, not one time generosity. At Smile Foundation, our efforts are to nurture long term partnerships by capturing impact progression over time.  Data driven insights have demonstrated how continued support helps in achieving compound outcomes. The focus is to create a shared legacy for a sustained impact, where partnerships and communities evolve and mature together. 

  • Timely Engagements During Moments That Matter 

By anticipating seasonal giving cycles like DaanUtsav, or responding swiftly during emergencies like floods in Punjab and Assam or festive engagements, Smile Foundation’s CRM mobilised swift support in partnership with brands. Such CRM collaborations helped in aligning real time needs, where our partners’s enthusiastic responsiveness transformed them from corporate entities to changemakers, standing alongside the communities during moments that are important. 

Smile’s CRM Drives Impact in 2025

Submarine Pens joined hands with Smile Foundation to create impact beyond the product. With Smile Foundation’s presence across 2,000+ villages and urban slums in India, this collaboration helps to extend access to education and healthcare for children who need it most. Each pen purchased becomes a symbol of shared responsibility—transforming everyday moments into opportunities for learning, wellbeing, and brighter futures. Together, the partnership demonstrates how conscious consumer choices can translate into lasting social change, touching lives with dignity, hope, and purpose.

  • Fashion with Intention, Impact with Meaning

The Lakshita–Smile Foundation partnership exemplifies purpose-led cause marketing, where responsible fashion was leveraged to create measurable social impact. Through a creative engagement initiative, children from Smile Foundation’s Mission Education Centres explored art, confidence, and self-expression using upcycled materials. The handcrafted creations were later showcased and sold at Lakshita stores, with proceeds supporting children’s education and wellbeing. This collaboration not only amplified brand purpose but directly enabled young learners to access opportunities, nurturing creativity while contributing to brighter, more sustainable futures.

  • Relationship-Led CRM for Women’s Health
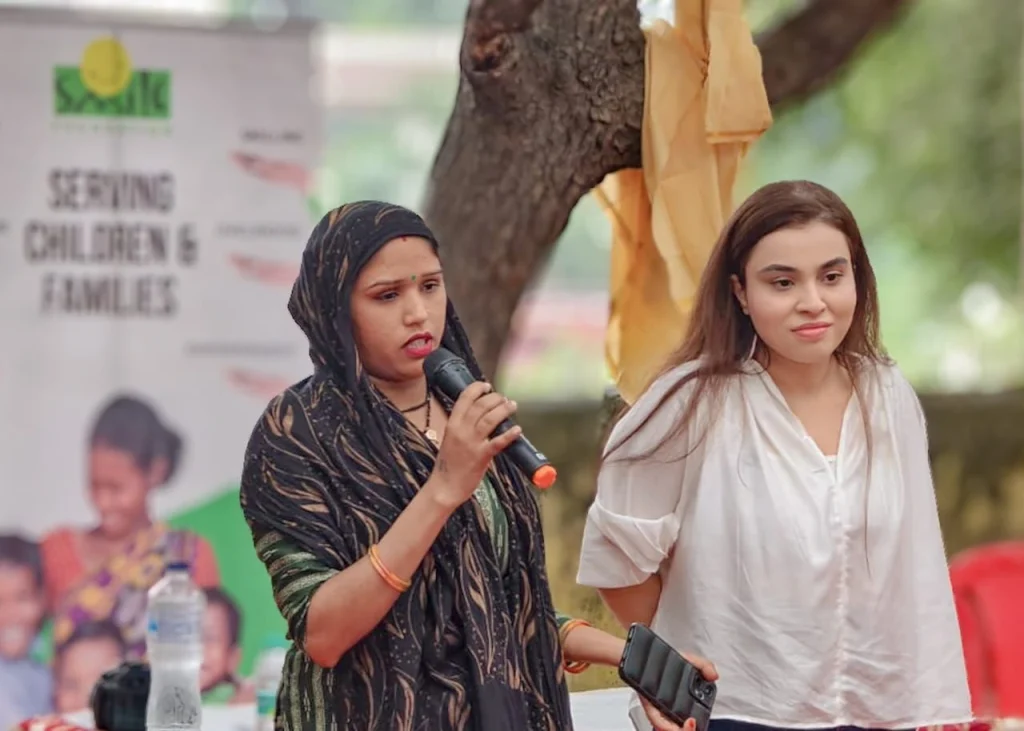
This CRM-led partnership with Amara Organics demonstrates how sustained corporate engagement can drive meaningful social outcomes. By co-creating a community outreach initiative on menstrual hygiene and reproductive health, the collaboration enabled open dialogue, trust-building, and awareness among women beneficiaries. Beyond education, the distribution of sanitary napkins ensured immediate access to essential care. Such engagements strengthen long-term relationships between corporates and communities, positioning cause-led events as strategic touchpoints that advance women’s health, reinforce partner commitment, and deliver measurable, people-centric impact through collaborative action.

  • CRM translates into Livelihood Outcomes

A placement drive under Smile Foundation’s skilling and livelihood initiative in Delhi, conducted in collaboration with Holiday Inn Express, enabled structured talent-matching for young aspirants entering the workforce. Supported by CRM-led coordination, the initiative ensured seamless partner engagement, candidate tracking, and outcome measurement. Through industry-aligned training in hospitality, retail, and BPO sectors, seven candidates secured placements, marking a significant step towards sustainable livelihoods. The collaboration highlights how data-driven partnerships and coordinated engagement can translate skilling interventions into measurable employment outcomes and long-term socio-economic empowerment.

Looking Ahead: Shaping a More Compassionate 2026

Smile Foundation’s partnership philosophy is anchored in deepening relationships rather than expanding numbers. Our focus remains on building collaborative partnerships that deliver sustained and measurable impact. Our Cause related marketing initiative functions as a strategic enabler with integrated insights, on-time responsiveness and accountability to support more human centered CSR engagements. By aligning partner objectives with on ground realities, CRM has strengthened trust and long term value creations for both brands and communities. This 2026, Smile Foundation’s CRM goals are committed to expand brands efforts to co- create impact through commitment, clarity and collective purpose. 

Be Part of Purpose-Driven CRM initiatives this year. Partner with Smile to empower lives with education, healthcare and livelihood.

Sources:

Categories
Health

Digital Health at the Last Mile and the Future of Public Health

Digital healthcare did not begin with artificial intelligence or mobile apps. Its earliest forms were far more modest: electronic registers replacing paper files, SMS reminders for appointments and basic teleconsultations bridging distance. Over time, these tools evolved into integrated systems capable of tracking patients, analyzing disease trends and strengthening accountability across health programmes.

For developing countries, this evolution has been neither linear nor optional but shaped by necessity.

In contexts where healthcare systems must serve large populations with limited infrastructure, uneven workforce distribution and persistent access gaps, digital health has emerged not as a luxury, but as a structural response to constraint.

The early phase: Digitisation as record-keeping

The first wave of digital healthcare focused on replacing paper-based systems. Electronic health records, digital registers and basic reporting tools helped standardise data and reduce loss of information. While these systems improved documentation, they did little to change how care was delivered on the ground.

In many low-resource settings, healthcare remained episodic — defined by camps, visits and one-time interventions. Records existed, but continuity did not.

This gap revealed a critical insight: digitisation without delivery integration does not transform health outcomes.

The shift toward integrated delivery

The second phase of digital healthcare marked a turning point. Technology began to move closer to patients into clinics, mobile units and community settings. Diagnostics became portable. Telemedicine connected frontline workers with doctors. Data began to flow in real time rather than months later.

This is where programme-led digital health models started to matter.

Organizations such as Smile Foundation demonstrate this evolution clearly. Its healthcare programme did not begin with technology adoption but with the need to deliver care consistently to underserved populations. Digital tools were introduced to strengthen continuity, coordination and accountability, not to replace human interaction.

Digital health, in the context of Smile Foundation’s healthcare work, is not positioned as a pilot project or an innovation layer added on top of existing services. Instead, it is treated as core infrastructure — the underlying system that enables scale, accountability and continuity of care. The healthcare model is designed as a digitally enabled last-mile system that integrates mobile service delivery, telemedicine, point-of-care diagnostics, electronic health records, GPS and attendance verification, and real-time disease surveillance. This integrated architecture is most clearly visible in the Smile on Wheels model, where physical mobility is combined with a robust digital backbone to ensure that care is not only delivered, but sustained.

Mobile units as connected health nodes

Within this system, mobile healthcare units are not standalone vans offering episodic services. Mobile Medical Units, Mobile Telemedicine Units, Mobile Dental Units, and Boat Clinics function as connected health nodes within a wider network. Every patient interaction is recorded through e-health records, with live capture of outpatient visits, diagnostics and prescriptions. Referrals to secondary and tertiary facilities are digitally tracked and disease trends are mapped across geographies. This transforms doorstep care from one-time outreach into longitudinal primary healthcare, a shift that remains uncommon in last-mile NGO health models.

Telemedicine as clinical backbone, not stopgap

Telemedicine plays a central role in maintaining this continuity. The programme uses ReMeDi, developed by NeuroSynaptic, as its clinical telemedicine backbone. ReMeDi enables real-time video consultations with doctors while automatically integrating more than 30 point-of-care diagnostic results into electronic medical records. Clinicians can review historical patient data during consultations, issue digital prescriptions and plan structured follow-ups. Importantly, telemedicine here is not limited to addressing doctor shortages; it supports specialist access, chronic disease management and continuity of care in aspirational and underserved districts.

Point-of-care diagnostics as field-level data engines

Diagnostics are another foundational element of the system. HealthCube, a portable point-of-care diagnostic hub, shifts testing closer to patients and reduces delays that often undermine treatment outcomes in rural health systems. HealthCube generates standardized, digitised diagnostic outputs within 3 to 15 minutes, covering vital parameters, biochemistry, infectious diseases and cardiac markers. These results are automatically fed into digital records, reducing repeat testing and enabling evidence-based decision-making. At a systems level, HealthCube functions as a field-level data engine, strengthening both individual care and population health analysis.

Governance, monitoring and accountability by design

Operational transparency and governance are built into the programme through digital monitoring systems. GPS and fleet-tracking tools provide real-time visibility into vehicle movement, geo-fenced service areas and trip summaries. Attendance verification through tools such as AngleCam captures time-stamped, location-based staff presence. Electronic health record dashboards offer HIPAA-compliant patient data, inventory management, donor-level access and live reporting. Together, these systems turn healthcare delivery into a verifiable and auditable operation, strengthening trust with donors, partners and government stakeholders.

The digital model also aligns closely with India’s national health architecture. While not branded as explicitly ABDM-centric, it supports ABHA ID facilitation, promotes awareness and enrolment under Ayushman Bharat and aligns referrals with public health facilities. This positions Smile Foundation as a complementary digital actor within India’s Universal Health Coverage framework rather than a parallel system operating in isolation.

One of the most significant strengths of this approach lies in its ability to close the loop between data and programme design. Field-level diagnostics generate structured data, which is analysed to identify disease patterns such as non-communicable diseases, tuberculosis, maternal and child health gaps and musculoskeletal disorders. Information, education and behaviour-change communication are then tailored to these patterns and preventive programmes are redesigned accordingly. This feedback loop is visible in expanded NCD screening, physiotherapy services driven by MSK disease prevalence and prioritization of oral health based on national and field-level gaps. Digital infrastructure thus informs programmatic decision-making.

Stress tests: Routine systems under crisis

The same digital backbone also supports emergency response. During disasters and the COVID-19 pandemic, digital systems enabled asset tracking for oxygen concentrators and medical kits, beneficiary mapping, coordination across more than 14 states and rapid reporting to donors and authorities. This demonstrates that the infrastructure supporting routine healthcare can also provide surge capacity during crises, a critical requirement in fragile and shock-prone settings.

Structurally, these elements show that Smile Foundation is not conducting health camps supported by technology. It is building a distributed digital health delivery system composed of modular service nodes, interoperable diagnostics, verifiable operations and population-level data intelligence. In infrastructure terms, this resembles a field-ready primary healthcare platform — one designed to deliver continuity, accountability and resilience at the last mile — rather than a conventional NGO health programme.

The future of last-mile healthcare

The future of healthcare in countries like India will not be decided solely by tertiary hospitals or national platforms. It will be shaped by how effectively care reaches people where they live, and whether it stays long enough to make a difference.

As countries invest in digital health, a shift in mindset is required. The question is no longer whether technology can improve care. It is whether digital systems are being designed as public goods — inclusive, interoperable, accountable and resilient.

Smile Foundation’s healthcare programme demonstrates that when delivery is prioritized and technology is thoughtfully integrated, last-mile healthcare can toward system-building. It shows that digital tools, when grounded in human-centred programmes, can transform access into continuity and presence into permanence.

In the end, the measure of digital health is not how advanced the technology is but whether it helps people live healthier lives, closer to home, with dignity and care that endures.

Categories
Smile

How 12th SIFFCY Uses Cinema to Build an Inclusive Generation

There are some films we never really outgrow. Not because they are childish, but because they were honest. They trusted young audiences with complex emotions. They refused to simplify the world. And in doing so, they shaped how we see difference, injustice, courage and hope.

A good film, watched at the right age expands our sense of who belongs.

That is the kind of cinema SIFFCY exists to celebrate.

Returning for its 12th edition from 28 January to 3 February 2026, SIFFCY — the Smile International Film Festival for Children & Youth — is back with the same conviction it began with: that children and young people deserve good cinema. Cinema that does not talk down to them. Cinema that opens doors instead of closing conversations and that reflects the world as it is, and as it could be.

An initiative of Smile Foundation, in partnership with the Department of Empowerment of Persons with Disabilities, Ministry of Social Justice & Empowerment, Govt of India and Delegation of the European Union to India, SIFFCY 2026 promises a week where films are screened and experienced through discussions, workshops, masterclasses and moments of shared discovery. This association brings a deeper context to the festival this year — one that foregrounds dignity, access and representation, both on and off the screen.

Image

Why Cinema Shapes How We Understand Difference

Cinema is often our first encounter with lives unlike our own. Long before textbooks teach us about inequality or inclusion, films allow us to feel it.

Think of The 400 Blows, which captured childhood restlessness and alienation with a tenderness that still resonates. Or Children of Heaven, where a lost pair of shoes became a lesson in dignity, siblinghood and resilience. Grave of the Fireflies showed that even animation could carry the weight of grief, asking young viewers not to look away from pain, but to sit with it.

These films did not explain the world but revealed it. SIFFCY curates cinema in this spirit — films that trust children and young people with emotional complexity, moral ambiguity and lived realities that stretch beyond their immediate surroundings.

12th SIFFCY: Inclusion as a Way of Seeing, Not a Checkbox

What makes 12th SIFFCY distinct is its insistence that diversity, equity and inclusion are not themes for a single panel or day, but a lens through which cinema itself is experienced.

Globally, some of the most influential films for young audiences have been those that challenged narrow ideas of ability, identity and belonging. Wonder reframed disability through everyday kindness rather than exceptionalism. Persepolis gave voice to a young girl navigating political upheaval with wit and courage. Capernaum forced the world to confront childhood lived without protection, through a lens that was unsparing yet deeply humane.

Indian cinema, too, has offered powerful examples. Stanley Ka Dabba spoke about hunger and exclusion without spectacle. Chillar Party celebrated collective action and difference with irreverent joy. Nil Battey Sannata challenged who gets to dream, and who gets to be taken seriously.

SIFFCY draws from this global and Indian cinematic vocabulary to help young audiences see difference not as a barrier, but as a shared human experience.

What the DEPwD Partnership Brings to SIFFCY 2026

The association with the Department of Empowerment of Persons with Disabilities adds a meaningful dimension to the 12th edition of SIFFCY. It reinforces a shared commitment to representation, access and dignity, and signals the importance of inclusive storytelling as a public value.

Through films that foreground ability, access and acceptance, SIFFCY 2026 aims to create a space where children and young people engage with disability not through pity or inspiration tropes, but through authenticity. These are stories where characters are not reduced to symbols and where lived experience takes precedence over labels.

In a country as diverse as India, where disability is still often spoken about in hushed tones or heroic clichés, such representation matters. Cinema, when curated with care, can help normalise difference, and in doing so, shape a generation that values equity instinctively.

Beyond Screenings: When Films Become Conversations

A film festival is not defined only by what plays on screen, but by what happens after the lights come on. SIFFCY has always understood this.

Alongside film screenings, the festival brings together panel discussions, workshops and masterclasses designed for children, young people, educators and emerging filmmakers. These sessions are not about decoding a “right” interpretation, but about encouraging questions. Why did a character choose silence? Who gets to be seen as the hero? What does access really mean in everyday life?

For anyone who has ever stayed back in a theatre lobby arguing about an ending, this is the real joy of cinema — watching meaning take shape through dialogue.

Access to Cinema Is an Inclusion Issue Too

Film festivals are often imagined as elite, urban spaces. SIFFCY has spent over a decade challenging this assumption.

Through outreach initiatives, school engagements and hybrid formats, the festival has reached children who may never have experienced global cinema otherwise. This matters deeply. Because access shapes imagination. And imagination shapes empathy.

By ensuring that carefully curated films travel beyond conventional cultural circuits, Smile Foundation positions cinema as a public good — something to be shared, questioned and lived with, rather than consumed in isolation.

Why SIFFCY Feels Urgent Right Now

Today’s young people are growing up amid climate anxiety, social polarisation, digital overload and constant visibility. The instinctive response is often to shield them or distract them. SIFFCY takes a more respectful approach: to engage them honestly.

Films that explore migration, disability, gender, conflict and belonging are not “too heavy” for young audiences. When framed thoughtfully and followed by conversation, they become tools for understanding a complicated world without fear.

This is why SIFFCY’s commitment to diversity, equity and inclusion feels especially timely. It offers a counterpoint to algorithm-driven content, reminding us that cinema can still be slow, reflective and deeply human.

For Those Who Fell in Love With Cinema Early

If you remember watching Cinema Paradiso and realising films could feel like memory or discovering Pather Panchali and understanding that silence can be as powerful as dialogue, SIFFCY will feel familiar. Not nostalgic, but alive.

This festival is for those who believe that cinema teaches us how to look at the world, and at each other, with more patience and care.

Save the Date

As SIFFCY enters its 12th edition, it continues to remain a space where meaningful storytelling shapes more inclusive ways of thinking, feeling, and belonging.

From 28 January to 3 February 2026, SIFFCY invites children, young people, educators, parents, filmmakers and cinema lovers to come together and watch the world unfold.

Because the films we watch when we are young do not just entertain us.
They might teach us who we might become.

📅 SIFFCY 2026 | 28 January – 3 February 2026

Learn more about SIFFCY here: https://www.smilefoundationindia.org/siffcy/

Categories
Smile

Story of Empowering Grassroots through CtGI

In India, grassroots organizations are often the first to respond when systems fail. They run schools in remote hamlets, organize women’s collectives, deliver health services where clinics don’t reach, and step in long before external funding arrives. But for all their proximity to communities, many of these organisations remain structurally fragile — dependent on short-term grants, foreign funding cycles or a small pool of donors far removed from the people they serve.

The challenge is not a lack of commitment or innovation. It is a lack of power — specifically, the power to mobilise resources locally, tell their own stories and sustain their work on their own terms.

This is the gap that Smile Foundation set out to address through its Empowering Grassroots programme and more recently through Change the Game India (CtGI) — the India adaptation of the global Change the Game Academy approach. At its core, CtGI is about shifting mindsets: from dependency to agency and external validation to local legitimacy.

Why local sustainability matters now more than ever

Over the past decade, India’s civil society landscape has undergone significant change. Regulatory shifts, shrinking international funding and heightened scrutiny have made it increasingly difficult for grassroots organizations to rely on traditional funding sources. At the same time, expectations on these organizations have only grown: deliver impact at scale, demonstrate accountability and respond to complex, overlapping crises — from climate stress to gender inequality.

What has not kept pace is investment in organizational capacity. Many community-based organizations are expected to perform like professional institutions without being equipped with the skills, systems or confidence to do so.

CtGI responds to this imbalance directly. Anchored within Smile Foundation’s Empowering Grassroots programme, it focuses on strengthening local fundraising, communication, planning and governance as core competencies. The idea is simple but powerful: if organizations can mobilize support from the communities they serve and the ecosystems they operate in, they become more resilient, more accountable and ultimately more effective.

Learning from the India story: when fundraising becomes community-building

One of the most compelling insights from the India chapter of the Voices of Change storybook is that the real impact of CtGI is relational.

Take the example of a women-led organization in rural Maharashtra, working with farmers and informal workers. Before engaging with CtGI training, fundraising was viewed as something external — grant proposals written for distant donors, often in language that did not reflect local realities. There was hesitation, even discomfort, around asking the community for support. After all, how do you fundraise among people who themselves have limited means?

CtGI challenged this assumption head-on. Through local fundraising training facilitated by Smile Foundation, the organization began to see fundraising not as extraction, but as participation. A community-led food festival, rooted in local culture and collective effort, became both a fundraising event and a public statement. It brought together women farmers, families, local leaders and supporters in a shared space of pride and ownership.

The funds raised mattered. But what mattered more was what followed: increased visibility, stronger trust and a shift in how the organisation was perceived — not as a beneficiary of aid, but as a credible local institution.

This is a recurring theme across India and Asia in the report. When organizations raise funds locally, they also raise confidence. They negotiate differently with partners. They plan with longer horizons. They are better positioned to say no to projects that don’t align with community priorities.

Reframing capacity building: skills, yes — but also power

Too often, capacity building in the development sector is framed narrowly: a workshop here, a toolkit there. CtGI takes a broader view. It recognizes that skills without confidence or systems without legitimacy, do not translate into sustainability.

By embedding CtGI within the Empowering Grassroots programme, Smile Foundation has been able to contextualise global learning for Indian realities. Training modules are adapted to local languages, social norms and funding ecosystems. Organizations are encouraged to experiment, reflect and iterate rather than replicate models designed elsewhere.

Importantly, CtGI also works with youth. Through its youth track, young people are introduced early to the idea that social change requires not only passion, but planning, communication and resource mobilisation. In a country with one of the world’s largest youth populations, this is a strategic investment in the future of civil society leadership.

Gender, dignity and local ownership

Another thread running through the India story is gender. Many of the organizations supported through CtGI work with, or are led by, women. For them, local fundraising is a financial tool and a pathway to visibility and voice.

When women organize public events, speak about their work and mobilize resources, they challenge entrenched ideas about who leads and who decides. In rural and semi-urban contexts, this visibility has ripple effects: shifting household dynamics, influencing local governance and inspiring younger women to step into leadership roles.

This aligns closely with Smile Foundation’s broader commitment to gender equity across its programmes. CtGI does not treat women as a “target group” but recognises them as central actors in building sustainable, community-rooted institutions.

From local roots to ecosystem change

While CtGI focuses on individual organizations, its implications are systemic. Locally sustainable organizations are better partners for government programmes. They reduce dependency on volatile funding flows. They contribute to a healthier civil society ecosystem — one where accountability flows both upwards to donors and outwards to communities.

The India experience also offers lessons beyond the country’s borders. Across Asia, from Sri Lanka to Cambodia, similar patterns emerge: when local organisations gain the tools to fundraise, communicate and plan strategically, they are better able to navigate uncertainty and assert their role as agents of change.

What distinguishes the Indian model is scale and localisation. By anchoring CtGI within a nationally rooted organisation like Smile Foundation, the programme benefits from deep contextual understanding and strong delivery networks. It is not a pilot on the margins but a growing movement within India’s development landscape.

A shift with lasting consequences

CtGI, through the Empowering Grassroots programme, is helping rewrite the story of grassroots work in India, from one of perpetual scarcity to one of shared responsibility. It reminds us that sustainability is not only about money. It is about dignity, trust and power.

As the development sector grapples with questions of localization, decolonisation and long-term impact, the lessons from Change the Game India are clear: when communities are trusted to fund, shape and sustain their own solutions, change is not only possible but durable.

And perhaps most importantly, it is owned by the people it is meant to serve.

Categories
Smile

India: An Exception to Asia’s Longevity Era

Asia is ageing at a speed without historical precedent. Japan, South Korea and China have moved from young to aged societies in a matter of decades, compressing demographic transitions that unfolded far more slowly in Europe. By 2050, more than a quarter of Asia’s population will be over 60, placing unprecedented pressure on labour markets, health systems and social protection frameworks.

India stands apart.

While its neighbours prepare for 100-year lives, India remains one of the youngest countries in the region. Its median age is still under 30, compared to over 48 in Japan and rapidly rising in China and South Korea. This demographic divergence positions India as both an outlier and a hinge point in Asia’s future: a country whose choices today will determine whether youth becomes a dividend, or a deferred burden.

Youth Is Not Immunity

India’s demographic youthfulness should not be mistaken for insulation from longevity challenges. Research from the UN Population Division shows that India will begin ageing rapidly after 2035, with the absolute number of older adults rising sharply even as the country remains younger, on average, than its neighbours.

What distinguishes India is timing. Unlike East Asian economies that aged before achieving universal health coverage or gender parity in the workforce, India has a narrow but critical window to prepare by investing in health, skills and social systems before ageing accelerates.

This window is especially consequential for women.

The Longevity Gap Is Gendered

Globally, women live longer than men but they also spend more years in poor health, unpaid care work and financial insecurity. In Asia’s ageing societies, women account for a disproportionate share of the elderly poor.

India’s younger age structure offers a chance to break this pattern early. However, evidence suggests that without intervention, the gendered longevity gap will persist.

The Global Burden of Disease (GBD) 2023 study shows that Indian women experience high years lived with disability due to anaemia, reproductive health conditions and non-communicable diseases beginning in midlife.

At the same time, labour force participation among Indian women remains among the lowest in Asia. OECD and ILO data consistently link women’s lifetime health and economic participation to better ageing outcomes, both at individual and societal levels.

How India supports women in their 20s, 30s and 40s will shape how the country ages decades later.

Learning from Ageing Neighbours — Before It’s Too Late

East Asia’s experience offers clear lessons.

Japan and South Korea built long life expectancy through strong public health and education systems, but entered ageing with rigid labour markets and deeply gendered care roles. China, despite rapid economic growth, faces a growing old-age dependency challenge as chronic disease and pension gaps converge.

Comparative research in The Lancet Healthy Longevity highlights that societies which failed to integrate women into paid work and preventive healthcare early now face higher long-term fiscal and care burdens.

India can chart a different path by aligning youth, women’s agency and health as a single strategy.

Health Today Is Longevity Tomorrow

Longevity is not built at age 60. It is accumulated across the life course.

WHO’s life-course health framework shows that nutrition, reproductive health, mental wellbeing and economic security in early and mid-adulthood are decisive determinants of healthy ageing.

India’s younger population means that investments in women’s health and prevention today have multiplicative returns: fewer chronic diseases later, lower dependency ratios and higher productive ageing.

This is particularly relevant in low-income and marginalised communities, where health risks accumulate earlier and ageing begins sooner in functional terms, even if chronological age remains low.

Women as the Bridge Between Demography and Development

From a macroeconomic perspective, women sit at the centre of India’s demographic advantage.

World Bank modelling shows that countries which combine demographic youth with higher female labour participation see sustained growth and slower ageing-related fiscal stress.

Women’s economic agency improves household nutrition, education and health outcomes — key inputs into a healthier future elderly population.

But this requires moving beyond episodic interventions toward integrated life-cycle support.

Grounding the Demographic Dividend in Community Systems

Evidence from implementation research shows that outcomes depend on whether services reach women where they live, work and care.

This is where organisations such as Smile Foundation play a structurally important role. Through women-centred initiatives that combine healthcare access, nutrition, livelihood support and education, Smile Foundation operates at the intersection where demographic potential is either realised or lost.

By strengthening women’s health, skills and agency during working years, such programmes shape India’s future ageing profile reducing vulnerability long before it appears in old-age statistics.

This is not social spending but longevity preparation.

Rethinking Longevity from a Young Country’s Perspective

Asia’s longevity narrative is often framed around retirement systems, pensions and eldercare. India’s contribution to this conversation must be different.

For India, the central question is not how to manage long lives but how to build healthy, productive ones early enough that ageing becomes manageable later.

This requires:

  • prioritising preventive health for women and adolescents
  • expanding women’s participation in paid and dignified work
  • reducing unpaid care burdens
  • embedding health and financial resilience across the life course

The evidence is that countries that act early age better.

A Window That Will Not Stay Open

India’s youth advantage is real but temporary.

Demography is destiny only if policy is absent. As neighbouring countries grapple with the costs of rapid ageing, India has a rare chance to prepare while it is still young.

Whether India becomes a country that ages before it grows old or one that transforms youth into lasting wellbeing will depend on how deliberately it invests in women today.

In an Asia defined by longevity, India’s exception may yet become its greatest contribution.

Categories
Gender

Women-Led Enterprises Critical for Rural Community Development

Across rural India, women-run enterprises generate income, stabilise household consumption, increase girls’ schooling, diversify local economies and anchor resilience during economic shocks. When they fail, the losses are not limited to jobs or output but ripple through nutrition, education, health and social cohesion.

Understanding why women-led enterprises matter, and what it takes to sustain them, is essential to any serious rural development strateg

Women’s Entrepreneurship as a Community Asset

Development economics has long shown that income controlled by women has different social effects than income controlled by men. Women are more likely to reinvest earnings in food, healthcare, education and housing — investments that strengthen human capital at the household and community level.

A large body of evidence supports this. Studies from the World Bank and IFPRI show that increases in women’s income are associated with improved child nutrition and educational outcomes, particularly in rural settings.

More recent cross-country analysis in World Development finds that women-owned enterprises generate higher local employment multipliers in low-income regions because they tend to source locally and retain earnings within the community.

In rural India, where formal employment opportunities are limited, women-led micro-enterprises often become economic anchors — small in scale, but large in impact.

Why Rural Women’s Enterprises Matter More Than Urban Ones

While women entrepreneurs operate across India, the developmental significance of women-led enterprises is particularly pronounced in rural areas.

Rural women face structural barriers like limited mobility, lower access to credit and restricted markets but they also operate in contexts where marginal gains have outsized effects. A tailoring unit, food-processing enterprise or agri-allied business can reshape household labour allocation, reduce distress migration and create local demand for services.

Research by the International Labour Organization shows that rural women’s enterprises are more likely than urban ones to employ other women and first-time workers, strengthening local labour participation.

This is why closures of women-led MSMEs matter so deeply. Each closure represents not only a failed business but a loss of local economic infrastructure.

Credit Alone Is Not Resilience

Government data shows substantial expansion in credit guarantees, procurement preferences and skilling programmes for women entrepreneurs. These interventions are necessary but evidence suggests they are not sufficient.

A 2023 systematic review in Small Business Economics finds that access to credit improves enterprise entry, but does not significantly improve survival rates unless paired with market access, mentoring and household-level support.

For rural women, enterprise fragility is often driven by factors outside the balance sheet: unpaid care work, health shocks, seasonal income volatility and social norms that limit decision-making authority. When crises occur through pandemics, climate shocks and price fluctuations, women-led enterprises are often the first to contract.

This explains why states with high concentrations of women-led MSMEs also report high numbers of closures. Density reflects participation; closures reflect vulnerability.

The Development Multiplier of Women-Led Enterprises

From a community development perspective, women-led enterprises generate three distinct multipliers:

  1. Household resilience
    Evidence from India and Bangladesh shows that women’s enterprise income reduces reliance on high-interest borrowing during shocks and improves food security during lean seasons.
  2. Human capital formation
    Girls in households with women entrepreneurs are more likely to remain in school, particularly at the secondary level, according to longitudinal studies in South Asia.
  3. Local economic diversification
    Women are overrepresented in sectors such as food processing, textiles, health services and education — sectors that stabilise rural economies and reduce dependence on single crops or employers.

These effects compound over time. When women’s enterprises survive, communities gain resilience. When they fail, vulnerabilities resurface quickly.

Why Survival Requires an Ecosystem, Not a Scheme

The emerging consensus in entrepreneurship research is clear: enterprise survival is ecosystem-dependent.

Women entrepreneurs benefit most from integrated models that combine:

  • basic finance
  • skills and business mentoring
  • market linkages
  • health and social protection

A 2024 UN Women report finds that women-led enterprises are significantly more likely to survive when livelihood support is combined with health access and social security, particularly in rural areas.

This is where civil society plays a structurally important role.

Linking Enterprise, Health and Agency at the Community Level

Organisations like Smile Foundation approach women’s entrepreneurship not as a standalone income intervention, but as part of a life-cycle development strategy.

Through its women-entrepreneurship and empowerment initiatives, Smile Foundation integrates livelihood training with health access, nutrition awareness, financial literacy and community mobilisation. This reflects a growing body of evidence that women’s economic agency is inseparable from health, time use and social norms.

Field studies consistently show that women are more likely to sustain enterprises when they have:

  • access to preventive healthcare
  • reduced care burdens
  • peer support and mentoring
  • confidence to negotiate markets and households

By embedding enterprise support within broader community development programmes, such models address the hidden constraints that credit and skilling alone cannot.

Rethinking Women-Led Enterprises as Rural Infrastructure

If India is serious about rural development, women-led enterprises must be treated as development infrastructure, not peripheral livelihoods.

This requires a shift in perspective:

  • from counting registrations to tracking survival
  • from credit disbursement to income stability
  • from enterprise numbers to community outcomes

It also requires recognising that closures are not merely business failures—they are signals of ecosystem stress.

The Stakes for Rural India

India’s rural future will be shaped not only by agriculture or large industry, but by millions of small enterprises that sustain everyday life. Women-led enterprises sit at the heart of this system.

When they thrive, communities gain resilience, children stay in school, nutrition improves and migration becomes a choice rather than a necessity. When they fail, the costs are borne by households, women and villages left more vulnerable than before.

Strengthening women-led enterprises is therefore not only about gender equity. It is about building rural economies that can endure.

And that makes women entrepreneurs the backbone of development.

Categories
Smile

FLN Is India’s Most Critical Investment in Its Future Workforce

India is often described as a future workforce superpower. By 2030, it will have the world’s largest working-age population. But demography alone does not create productivity. Skills do.

But India’s workforce challenge lies in a less visible but decisive constraint: foundational literacy and numeracy (FLN). These basic capabilities of reading with comprehension and working with numbers are not early learning milestones to be “completed” by age ten. They are the load-bearing foundations of every advanced skill, from digital fluency and vocational training to adaptability in a fast-changing labour market.

Global evidence increasingly shows that without strong FLN, investments in skilling, digital transformation and future-of-work initiatives deliver diminishing returns. For India, where learning deficits emerge early and compound over time, FLN may be the single highest-return investment for long-term economic growth.

The Learning Crisis Beneath the Skills Conversation

India’s learning challenge is well documented. The 2023 ASER report found that only about 43% of children in Class 5 could read a Class 2-level text and basic arithmetic proficiency remains similarly low. These gaps do not disappear with age; they harden.

International research confirms this pattern. The World Bank’s State of Global Learning Poverty estimates that 70% of children in low- and middle-income countries cannot read a simple text by age 10, with long-term consequences for productivity and earnings.

From a workforce perspective, this matters because skills build cumulatively. Cognitive science shows that higher-order skills like problem-solving, digital literacy and technical training depend on early mastery of reading and numeracy.

In other words, a weak FLN base constrains the effectiveness of every subsequent investment in human capital.

FLN as an Economic Multiplier

Education economists increasingly frame FLN as a macro-critical variable.

A landmark study by Hanushek and Woessmann shows that improvements in basic cognitive skills are strongly correlated with long-run GDP growth — more so than years of schooling alone.

More recent modelling in The Lancet estimates that closing foundational learning gaps could generate trillions in lifetime earnings globally, with especially large gains in countries with young populations.

For India, this implies that FLN is both a social investment and a growth capital. Every cohort that enters the labour force without basic literacy and numeracy represents lost productivity, lower adaptability and higher vulnerability to automation.

The Workforce Consequences of Weak Foundations

The future of work is often framed around AI, automation and digital skills. But evidence from labour economics suggests that workers with weak foundational skills are the most exposed to technological displacement.

OECD research shows that adults with low literacy and numeracy are significantly less likely to benefit from digital upskilling programmes and more likely to be trapped in low-wage, informal employment.

In India’s context, where over 80% of employment remains informal, weak FLN limits mobility even within low-skill sectors. Workers struggle with written instructions, basic financial calculations, safety protocols and digital interfaces increasingly embedded in logistics, manufacturing and services.

This is why skilling initiatives that bypass FLN often underperform. Training cannot substitute for foundations it assumes already exist.

Why Early Intervention Delivers the Highest Returns

Neuroscience and developmental economics converge on a clear insight: returns to learning investments are highest in early childhood and primary school.

James Heckman’s work on skill formation demonstrates that early cognitive skills make later learning more efficient; remediation becomes costlier and less effective over time.

In India, delays in foundational learning often stem from first-generation schooling, language barriers, malnutrition and inconsistent early schooling. These challenges disproportionately affect children from low-income and migrant families — precisely those who will form the bulk of the future workforce.

Targeting FLN early is therefore not only equitable, but economically rational.

FLN and the Digital Economy: A Hidden Dependency

India’s digital public infrastructure — from payments to health records — is often cited as a global model. But digital inclusion depends on the ability to read, interpret and act on information.

Studies on digital adoption show that literacy is a stronger predictor of effective technology use than device access alone.

Without FLN, digital tools risk widening inequality rather than reducing it. Workers may be connected but not empowered; enrolled but not capable of navigating systems independently.

Seen this way, FLN is a prerequisite for inclusive digital growth.

Why Delivery Matters

India has recognised the centrality of FLN through policy initiatives such as the National Education Policy (NEP) 2020 and the NIPUN Bharat Mission. The challenge now lies in execution — particularly in communities where schools face teacher shortages, high student mobility and limited parental support.

Global evidence suggests that community-embedded models combining classroom instruction with parental engagement, remediation and contextual learning are most effective in accelerating foundational skills.

This is where civil society plays a critical role as an implementation partner.

Bridging the Last Mile: Community-Led FLN in Practice

Organisations like Smile Foundation operate at the intersection of education, nutrition and social context where foundational learning outcomes are actually shaped.

Through school-based programmes, remedial learning, teacher support and parental engagement in underserved communities, Smile Foundation’s education initiatives address the non-academic barriers that undermine FLN: poor nutrition, irregular attendance, language gaps and lack of learning support at home.

This integrated approach reflects findings from implementation research showing that learning outcomes improve when education interventions are paired with health, nutrition and family engagement.

By stabilising learning environments and supporting early mastery, such models increase the likelihood that children transition into secondary education with the skills needed to benefit from further training.

FLN as a National Workforce Strategy

Countries that succeed in the future economy will be those that ensure:

  • early mastery of literacy and numeracy
  • smooth transitions from school to skill development
  • continuous learning across the life course

India’s scale magnifies both risk and opportunity. Small improvements in foundational learning, applied across millions of children, generate outsized economic returns.

Investing Where the Compounding Begins

The most powerful investments are those that compound over time. Foundational literacy and numeracy do exactly that persistently, and across generations.

If India’s ambition is to build a resilient, adaptable and productive workforce, the starting point is not the factory floor or the coding bootcamp. It is the primary classroom, the community learning centre and the child learning to read with confidence and count with understanding.

That is where the future workforce is already being shaped.

Categories
Health

Health Dividend: Do Digital Health Investments Actually Pay Off

The case that health is a high-return investment is now well established. Preventive care improves productivity, reduces avoidable costs and strengthens human capital. Digital health systems — when interoperable and widely adopted — can amplify these gains by reducing waste, improving access and enabling earlier intervention.

India’s digital health push has been cited as early evidence that this model can scale. But the more difficult question comes after proof of concept: what determines whether health and digital health investments actually deliver sustained economic and social returns?

Recent research suggests that returns are neither automatic nor evenly distributed. They depend on where investments are made, who they reach and whether health systems are strong enough to convert digital capacity into real outcomes.

From Infrastructure to Impact: Why Digital Alone Is Not Enough

Digital health infrastructure lowers transaction costs and improves system efficiency but only when paired with functional care delivery. Health economists increasingly warn against “digital overbuild”: systems that generate data faster than they generate care.

A 2023 review in The Lancet Digital Health found that while digital tools improve screening, follow-up and provider productivity, their impact on morbidity and mortality is contingent on underlying primary healthcare capacity including trained staff, medicines and referral pathways.

In low- and middle-income settings, digital systems often succeed in urban and tertiary care environments first, where institutional capacity already exists. Returns are highest where digital tools close gaps, not where they merely optimise already well-resourced services.

This distinction matters for India, where regional variation in health system strength remains substantial.

The Productivity Channel: Health Dividend and Gains Must Reach the Workforce

One of the strongest arguments for health investment is its effect on labour productivity. But productivity gains accrue only when healthier years are added within working life.

The Global Burden of Disease (GBD) 2023 update shows that India’s gains in life expectancy are increasingly offset by years lived with disability, driven by non-communicable diseases such as diabetes, cardiovascular disease and chronic respiratory illness.

This means that digital health investments that focus on early detection, continuity of care and chronic disease management are far more likely to yield economic returns than those focused solely on episodic care.

A World Bank working paper (2024) estimates that improving NCD control in working-age populations could raise GDP growth by up to 1.5 percentage points annually in middle-income countries but only if care pathways reduce long-term disability.

Health investment yields returns only when it prevents households from falling into poverty.

Despite expanded insurance coverage, out-of-pocket expenditure remains a dominant feature of India’s health system. A 2024 Scientific Reports study confirms that catastrophic health spending continues to affect over 75% of cancer-affected households, with diagnostics and medicines as major cost drivers.

Digital claims processing and interoperable records can reduce administrative friction but financial protection fails when diagnostics, transport and outpatient care remain uncovered.

Health economists increasingly argue that digital efficiency without financial risk protection produces asymmetric returns: system savings accrue to institutions, while households remain vulnerable.

For digital health to deliver inclusive returns, it must be embedded in benefit design that protects households across the care continuum.

Equity Determines Scale

A consistent finding across recent studies is that equity is not a moral add-on but an economic multiplier.

A 2023 McKinsey Health Institute analysis shows that health investments targeting underserved populations generate higher marginal returns because baseline health deficits are larger.

Similarly, WHO’s Global Report on Universal Health Coverage (2023) finds that investments in primary care and community health yield stronger long-term fiscal returns than hospital-centric spending.

This evidence explains why community-embedded models where digital tools are paired with outreach, screening and navigation consistently outperform technology-only approaches.

Interoperability Is an Economic Choice for Health Dividends

Interoperability is often discussed as an IT challenge. In reality, it is an economic one.

Fragmented systems impose recurring costs: duplicate diagnostics, delayed referrals, and preventable complications. A 2024 OECD report estimates that 20–40% of health spending globally is lost to inefficiency, much of it due to information silos.

India’s experience with shared digital rails shows how interoperability changes incentive structures. When providers can access records across settings, follow-up improves and unnecessary repeat tests decline — key drivers of cost containment.

However, international experience suggests that interoperability must be governed, not merely enabled. Without standards for data quality, privacy and clinical accountability, systems risk becoming repositories rather than decision tools.

Why Prevention Delivers the Highest Compound Returns

Among all health investments, prevention produces the most durable returns but often the least immediate visibility.

A 2023 modelling study in The Lancet Public Health estimates that scaling preventive interventions for hypertension, diabetes and tobacco use in South Asia could avert over 10 million premature deaths by 2040, with benefit–cost ratios exceeding 10:1.

Digital tools enhance prevention by enabling:

  • population-level risk stratification
  • reminders and follow-up
  • longitudinal monitoring

But prevention works only when trust exists. Community-based engagement remains essential for uptake, especially among women, migrants and informal workers.

The Role of Civil Society in Unlocking Returns

Evidence from implementation science shows that digital health adoption accelerates when civil society bridges the last mile supporting awareness, navigation and continuity.

Models that integrate digital systems with community outreach help ensure that investments reach populations most likely to generate high marginal gains. This is where organisations like Smile Foundation become structurally relevant as system enablers.

By linking health education, screening, referral and follow-up within underserved communities, such approaches improve utilisation of digital and public health infrastructure already in place.

From Health Spending to Health Capital

The emerging consensus in health economics is that health delivers returns when treated as capital, not consumption.

Capital investments require:

  • time horizons longer than electoral cycles
  • outcome tracking, not activity counts
  • alignment between digital systems, financing and care delivery

India’s experience shows that the building blocks exist. The challenge now is to ensure that digital health investment translates into longer healthy working lives, lower household vulnerability and sustained productivity gains.

The health dividend is real but it is not automatic. It compounds only when systems are designed to include those who need care the most, not just those easiest to reach.

That is where the next phase of India’s health story will be decided.

Categories
Health

Women, Cancer and Survival in Urban Slums

In India’s cities, cancer is increasingly common, increasingly visible, and still, too often, discovered too late. For women living in urban slums, the story of cancer is one about indefinite delay: delays in recognising symptoms, in seeking care, in being taken seriously and in reaching treatment before options narrow.

Breast cancer is now the most frequently diagnosed cancer among Indian women. Oral cancers, strongly linked to smokeless tobacco and areca nut use, are disproportionately concentrated in low-income communities. Cervical cancer persists where routine screening remains inaccessible. Together, these cancers account for a significant share of morbidity and mortality among women, even as early detection could substantially improve outcomes.

India recorded an estimated 1.46 million new cancer cases in 2022, with projections indicating continued increases through 2025, according to the National Cancer Registry Programme. Breast cancer alone contributes a major share of cancer-related deaths among women, while cervical cancer continues to place India among the highest global contributors to disease burden. Oral cancers, particularly prevalent in South Asia, remain among the leading causes of cancer mortality nationally.

Incidence tells only part of the story. The more decisive factor in survival is stage at diagnosis. And for women in urban informal settlements, that stage is often late.

When illness competes with everyday survival

In dense urban settlements, symptoms rarely present as medical emergencies. A breast lump may be painless. Oral lesions may be dismissed as tobacco-related irritation. Abnormal bleeding is often normalised or hidden. When illness competes with daily wage work, childcare and food insecurity, it is postponed — sometimes indefinitely.

Compounding this is multimorbidity. Diabetes, hypertension, tuberculosis and anaemia are common in slum populations and frequently coexist with cancer. These conditions not only mask early cancer symptoms but delay referrals and complicate treatment pathways. By the time cancer is suspected, households are already financially and physically depleted.

The economic consequences are severe. Cancer treatment in India involves high out-of-pocket expenditure, with annual direct costs averaging over ₹3 lakh per patient. Diagnostics and medicines account for much of this burden. Studies show that more than three-quarters of households affected by cancer experience catastrophic health spending, often resorting to borrowing or asset sales. For women whose healthcare decisions are mediated by household finances, this economic reality shapes whether care is pursued at all.

Belief, stigma and the cost of waiting

Biomedical explanations for illness do not operate in isolation in India’s cities. In urban slums, traditional beliefs coexist with modern medicine, often shaping when and how care is sought.

Fatalistic thinking — expressed as “what will be, will be” — has been repeatedly documented as a reason for postponing medical attention for serious symptoms. Research links such beliefs to longer diagnostic delays and poorer outcomes for cancer and other chronic diseases. These delays are reinforced by poverty, limited access and fear of financial ruin.

For women, stigma adds another barrier. Breast and reproductive symptoms are often concealed due to modesty, fear or social norms around exposure and examination. Awareness of early warning signs remains low and many women report reluctance to undergo physical examinations. When symptoms are invisible to others, silence becomes easier than disclosure.

The first stop is rarely the clinic

Health-seeking in urban poor communities often begins outside the formal medical system. Informal practitioners, traditional healers and ritualistic providers frequently serve as first points of contact. Evidence from multiple Indian studies shows that initial reliance on non-biomedical providers is associated with substantial delays in reaching formal care.

This pattern is not unique to cancer, but its consequences are particularly severe for diseases where early intervention is critical. Each additional step before reaching a qualified provider narrows the window for curative treatment.

When autonomy is limited, so is care

Gendered power dynamics further shape outcomes. National data show that nearly one in three ever-married women in India has experienced physical or sexual violence by a spouse. While urban averages may appear lower, studies consistently report higher prevalence in slum settings, alongside controlling behaviours that restrict mobility, finances and decision-making.

These conditions make healthcare conditional on permission, affordability and silence. Research links restricted autonomy directly to later-stage cancer diagnosis among women. Myths around cancer treatment like surgery causes loss of womanhood, chemotherapy hastens death — reinforce fear and lead to refusal or abandonment of care, especially where misinformation spreads quickly through close social networks.

Administrative invisibility and fragmented care

Urban slums are also shaped by migration. Many women lack local identity documents or ration cards, making insurance enrolment difficult and care discontinuous across cities. While India’s health insurance coverage has expanded in recent years, utilisation remains uneven. Even when hospitalisation is covered, out-of-pocket expenses for diagnostics, medicines, transport and informal fees persist.

The result is fragmented care — diagnosis without follow-up, referral without treatment and treatment without continuity.

What changes when care comes closer

Evidence from public health consistently shows that proximity matters. When services move closer to homes, delays shorten. When trust is built through repeated engagement, stigma weakens. When women encounter care in familiar spaces, fear becomes manageable.

Community-based models that combine health education, screening and navigation support have demonstrated measurable improvements in health-seeking behaviour. Programmes such as Swabhiman, run by Smile Foundation, illustrate this approach by embedding health outreach within broader efforts to strengthen women’s autonomy, nutrition and economic participation. By using trained community educators and health camps as entry points, such models address not only awareness gaps but the structural barriers that delay care.

Importantly, these interventions do not frame women as passive recipients of care, but as participants capable of recognising symptoms, supporting peers and navigating systems when given the tools to do so.

The unfinished work of early detection

India’s cancer burden is often discussed in terms of numbers — incidence, mortality, projections. But for women in urban slums, the decisive factor remains whether early signs are noticed, named and acted upon.

Early detection is not a technological challenge alone. It is a social one that requires addressing fear, misinformation, financial precarity and gendered constraints alongside expanding services. Without this, advances in treatment will continue to bypass those who need them most.

Cancer outcomes in urban India will not improve through hospitals alone. They will improve when care becomes visible before disease becomes advanced — when women are supported to speak, to seek and to survive.

That work is slow, local and unglamorous. But it is where survival is decided.

Categories
Nutrition

Mapping Seasonal Nutrition: What Indian Families Should Eat

For centuries, Indian diets evolved not from nutrition charts but from agro-ecological logic. What people ate was shaped by what the land could produce at a given time, how crops responded to heat or rain and what the human body could digest under those conditions. Seasonal eating was not cultural preference alone; it was a risk-management strategy in an environment defined by climatic variability.

Seasonal nutrition is the point where crop cycles, climate stress and human health intersect. Today, that intersection is under strain. Climate change is disrupting sowing calendars, altering crop yields and weakening the natural alignment between seasons and diets. At the same time, India faces a dual nutrition crisis: persistent undernutrition and anaemia alongside rising obesity and diet-related diseases.

Relearning how to eat with the seasons is about nutritional resilience in a changing climate.

Why Seasonal Nutrition Is Agronomically Sound

Seasonal foods are not just fresher — they are biologically and nutritionally superior. Crops grown in their natural season tend to have higher micronutrient density, lower pest pressure and reduced reliance on chemical inputs. From a food-systems perspective, this translates into affordability, accessibility and nutritional reliability.

Human digestion also follows seasonal patterns. Heat, humidity and cold influence appetite, gut motility and metabolic demand. Nutrition science increasingly recognises that dietary adequacy is context-dependent, not static.

When diets drift away from seasonal availability — replaced by ultra-processed foods or transported produce — nutrient intake often worsens, particularly for low-income households.

Climate Change Is Disrupting Seasonal Food Logic

India’s climate is no longer predictable. Heatwaves are longer, monsoons erratic and winters uneven. These shifts affect not only how food is grown but which foods remain accessible at what price.

Research shows that climate variability is already reducing the availability of fruits, vegetables and pulses which are key sources of micronutrients, especially in rain-fed regions. When harvests fail or prices spike, families substitute with calorie-dense but nutrient-poor foods.

Children, pregnant women and elderly populations are most affected. Seasonal nutrition, therefore, must now be understood as adaptive nutrition — a way to buffer households against climate-induced food stress.

Summer: Hydration, Crop Water Stress and Light Diets

Indian summers coincide with peak crop water stress and the lean period between rabi harvest and kharif sowing. High temperatures increase water loss in both crops and people.

Agronomically, summer vegetables like gourds, cucumbers and melons have high water content and shorter growing cycles, making them nutritionally and ecologically efficient. Nutritionally, these foods support hydration, electrolyte balance and digestive ease.

Fermented dairy products such as curd and buttermilk support gut health and reduce heat stress, a finding supported by microbiome research.

But access remains unequal. In urban slums and drought-prone villages, fresh produce is often unaffordable or unavailable. This is where nutrition education must be paired with access.

Through community nutrition programmes, Smile Foundation promotes low-cost summer diets using locally available foods linking agricultural seasonality with household practice rather than prescribing idealised food lists.

Monsoon: Disease Ecology and Dietary Safety

The monsoon is agronomically productive but biologically risky. Warm, wet conditions favour crop growth and pathogens.

From a food-systems lens, monsoon diets should prioritise digestibility and safety. Pulses like moong, rice-based meals and cooked vegetables reduce gastrointestinal stress. Spices such as turmeric and ginger have well-documented anti-inflammatory and antimicrobial properties.

Public health data consistently link monsoon diarrhoeal disease with seasonal undernutrition, especially among children. Nutrition setbacks during this period can erase months of growth gains.

Smile Foundation’s mobile health and nutrition outreach during monsoon months focuses on hygiene, safe cooking practices and immunity-supporting diets — an approach aligned with evidence that nutrition counselling reduces seasonal morbidity.

Winter: Energy Density and Nutrient Replenishment

Winter coincides with peak availability of leafy greens, pulses and oilseeds — nutritionally dense crops well suited to cooler temperatures. From an agricultural perspective, this is the recovery season.

Leafy vegetables such as spinach and mustard greens are rich in iron and folate. Pulses and legumes restore protein deficits. Oilseeds like sesame and groundnut provide essential fatty acids and caloric density.

Traditional winter foods — jaggery, sesame laddoos, slow-cooked saag — are examples of climate-responsive diets. However, winter also exposes inequalities. For migrant workers and homeless populations, cold stress coincides with food insecurity.

Seasonal feeding programmes that provide warm, calorie-dense meals during winter are therefore not charity, but nutritional correction. Smile Foundation’s winter nutrition initiatives and anaemia screening programmes address precisely this seasonal deficit.

Women, Children and Seasonal Nutritional Risk

Agricultural and nutrition data consistently show that women and children experience seasonal food stress most acutely. Pregnant and lactating women require different nutrients across seasons. Children are vulnerable to growth faltering during illness-heavy months.

Gendered food allocation where women eat last and least magnifies seasonal deficits. Seasonal nutrition education targeted at mothers has been shown to improve child dietary diversity and reduce anaemia.

By linking school meals, maternal counselling and community agriculture awareness, Smile Foundation applies a life-cycle nutrition approach grounded in food-systems science.

Seasonal Nutrition as Climate Adaptation

From an agricultural standpoint, seasonal nutrition is not about returning to the past. It is about aligning diets with ecological reality in a climate-unstable future.

Seasonally appropriate diets:

  • reduce dependency on volatile food markets
  • lower household food costs
  • improve micronutrient intake
  • increase resilience during climate shocks

FAO increasingly recognises dietary diversification and local food systems as key climate adaptation strategies.

Toward a Seasonal, Equitable Nutrition Future

Seasonal nutrition sits at the intersection of agriculture, climate science and public health. It does not require supplements or imported foods, but knowledge, access and institutional support.

When families understand what to eat, and can afford it, nutrition improves. When community organisations translate food-system science into daily practice, resilience follows.

Reconnecting Indian diets with seasons is not nostalgia. It is evidence-based adaptation. And in an era of climate uncertainty, it may be one of the most practical nutrition strategies we have.

0%


